How Does the Brain Form Habits?
A Habit Has a Precise Definition — and It’s Not “Something You Do a Lot”
A habit forms when a behavior that starts out as a deliberate, goal-directed action gradually becomes triggered automatically by a cue in the environment, with less and less input from conscious deliberation about the outcome. In behavioral neuroscience, that’s a precise, testable definition — an instrumental behavior that has become insensitive to the current value of its outcome, triggered relatively automatically by a stimulus or context — not just a loose way of describing something you do often. Goal-directed action, by contrast, stays sensitive to both the current value of its outcome and the causal link between the action and that outcome. These aren’t two separate behaviors; they’re two different modes of controlling the same behavior. Reaching for a snack can be goal-directed early in learning and habitual after extended, consistent practice — the action looks identical, but what’s driving it has changed. This framework comes primarily from instrumental (operant) learning theory and animal behavioral neuroscience — well-supported, but a simplified model that doesn’t capture every everyday use of the word “habit” (habits of thought or complex social habits are studied differently).
Circuits, not a single “habit center”
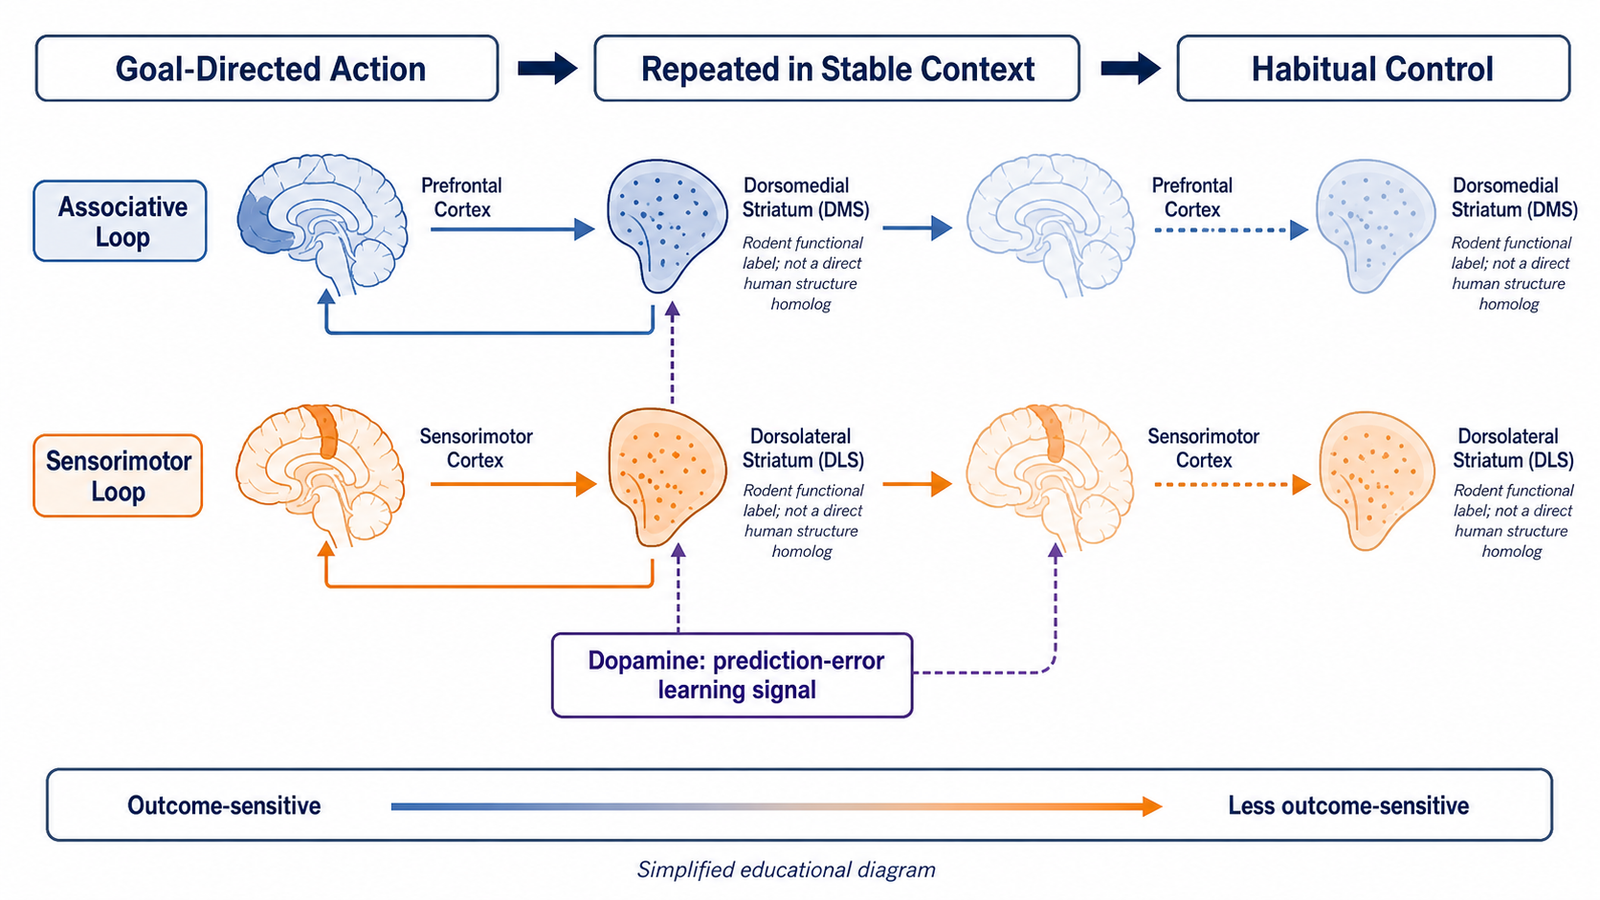
It’s tempting to say “the basal ganglia control habits,” but the evidence points to something more specific and more distributed. Different loops within the cortico-basal ganglia-thalamocortical system are associated with different modes of behavioral control, and no single structure acts alone. Rodent lesion and inactivation studies show a double dissociation: damaging or inactivating the dorsolateral striatum keeps behavior goal-directed even after extended training, while damaging or inactivating the dorsomedial striatum causes behavior to become habitual earlier than normal. Two independent lines of evidence pointing the same direction is part of why researchers are confident these are genuinely separable circuits rather than one region doing everything. It’s also worth being precise about what the basal ganglia even are: a group of interconnected subcortical nuclei — striatum, globus pallidus, subthalamic nucleus, substantia nigra — not a single structure, and they participate in plenty besides habit, including movement selection and motivation. Cortex, thalamus, and even the hippocampus participate in these loops too, which is why “a basal ganglia function” undersells what’s really a cortico-striatal-thalamic loop system with regionally specialized subdivisions.
Dopamine is a learning signal, not “the habit chemical”
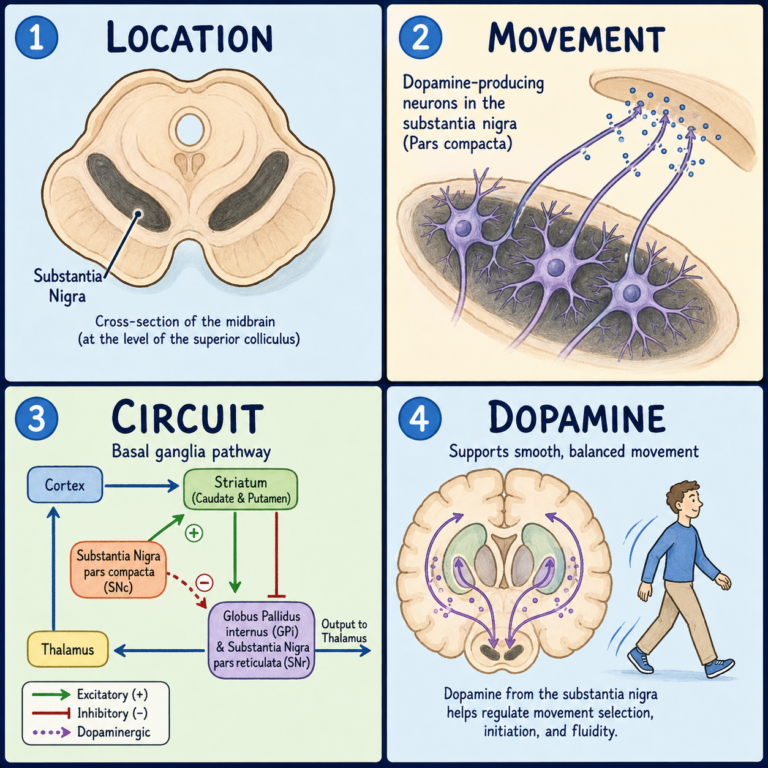
Early theories treated dopamine release as a direct signal of pleasure. Landmark 1990s electrophysiology work — recording from dopamine neurons in monkeys performing learning tasks — showed something more specific: dopamine neurons fire in proportion to a reward prediction error, the gap between the reward received and the reward expected. An unexpected reward produces a burst of dopamine activity; a fully expected reward produces little to no burst; an expected reward that fails to arrive produces a dip below baseline firing. That prediction-error signal functions as a teaching signal strengthening or weakening the associations underlying both goal-directed and habitual learning, depending on which circuit is being updated — which makes both “the pleasure chemical” and “the habit chemical” inaccurate shorthand. Dopamine doesn’t map onto subjective pleasure in any simple one-to-one way, and it contributes to reinforcement learning broadly — goal-directed learning, motor learning, motivational salience — not habit formation specifically. A thermostat’s error signal is a useful partial analogy: it doesn’t “feel” warm or cold, it just adjusts future heating based on the gap between target and actual temperature. But the analogy breaks down once you factor in how dopamine signaling also interacts with motivation, effort, and salience in ways a thermostat simply doesn’t.
How a behavior actually shifts from goal-directed to habitual
A behavior is first tried because it’s expected to produce a valued outcome — control is largely goal-directed here, engaging the associative circuit linked to the dorsomedial striatum. As the behavior repeats in a stable cue-context (same time, place, or preceding trigger), synaptic changes in sensorimotor corticostriatal circuits, including the dorsolateral striatum, are associated with the behavior becoming more reliably triggered by the cue itself rather than by a decision. Laboratory tests eventually show the behavior increasingly persists even when the outcome has been devalued — sating an animal on the specific food it normally works for, say, or pairing that outcome with illness. What results is a relative shift, not a full replacement, of control: habitual, sensorimotor circuits take on more of the load, but goal-directed circuits aren’t deleted. Under sufficient attention, effort, or a strongly conflicting incentive, more deliberate control can often reassert itself — though exactly how much of that flexibility exists in humans specifically is still an active research question.
The way researchers actually test whether a behavior has become a habit is called outcome devaluation, and it’s worth understanding because it’s the operational definition behind everything above — not a subjective judgment about whether a behavior “looks” automatic. An animal is trained to perform an action for a food reward. Later, that food is devalued — by feeding the animal to satiety on it, or pairing it with mild illness — without letting the animal perform the action again first. Then the animal gets a chance to perform the action with no reward delivered at all (an extinction test), and researchers watch what happens: if the animal performs the action less, its behavior was still goal-directed; if it keeps performing at a similar rate, its behavior had become a habit.
Where this framework helps clinically — and where it doesn’t
Understanding habit circuitry is relevant to several areas of medicine and health science, but each application carries real limits that shouldn’t be overstated in patient-facing communication. In addiction, some researchers propose that as substance use progresses, control can shift from goal-directed, ventral-striatal-linked drug seeking toward more dorsal-striatal, habit-like — and eventually compulsive — drug-seeking that persists despite negative consequences. It’s an influential framework, but addiction involves additional processes — withdrawal, craving, altered stress and prefrontal regulation — that aren’t reducible to “habit” alone, and much of the direct circuit evidence again comes from animal drug-self-administration studies. Basal ganglia circuit dysfunction is implicated in some obsessive-compulsive and tic-related behaviors too, but compulsions in OCD aren’t simply habits — they’re typically accompanied by distressing intrusive thoughts and anxiety-driven relief-seeking, a different psychological process from an automatic stimulus-response habit. Recent preclinical work — currently a preprint, not yet fully peer-reviewed — has even suggested some forms of striatal dysfunction can produce excessive goal-directedness and rigidity rather than pure habit dominance, meaning the compulsion-habit relationship is more complicated than one linear model can capture. Diseases affecting the basal ganglia, like Parkinson’s or Huntington’s disease, can affect the acquisition or automatic execution of learned motor sequences — consistent with the basal ganglia’s broader role in action selection, but a separate topic from everyday habit change that shouldn’t be conflated with it. And cue-based, context-consistent repetition strategies used in behavior-change programs — “always do X after Y” — draw conceptual support from this literature, but real-world behavior change also depends on motivation, environment, and social support well outside the scope of striatal circuitry alone.
None of this is a treatment guideline, and it shouldn’t be used for individual diagnosis or treatment decisions. Anyone with clinically significant compulsive behavior, substance use concerns, or a movement disorder should be directed to an appropriate clinician rather than a neuroscience explainer.
What the “66 days” claim actually comes from
There’s no single fixed number for how long habit formation takes, despite how often one gets quoted. The most-cited real-world study found a median of about 66 days for simple daily behaviors to reach a plateau of automaticity, with an observed range of roughly 18 to 254 days depending on the behavior and the person (Lally et al., 2010) — one relatively small study, worth treating as an estimate rather than a rule. It’s also worth distinguishing this from the popular “cue-routine-reward” habit loop framing from general-audience books: that’s a simplified, accessible version of the same underlying stimulus-response and reinforcement-learning concepts described above, useful as teaching shorthand, but not a formal neuroscience term, and it doesn’t capture the circuit-level distinctions — dorsolateral versus dorsomedial striatum, dopamine’s prediction-error role — that the research actually turns on. And in controlled experiments, habitual responding can be reduced, through extinction training or by deliberately reinstating goal-directed attention, but that’s more clearly demonstrated in animal studies than guaranteed in everyday human behavior change, which depends on plenty outside brain circuitry alone.
This article is intended for general medical, nursing, and health-science education, not individualized clinical assessment or treatment. If someone’s repetitive or compulsive behaviors are causing significant distress, interfering with daily functioning, or related to substance use, encourage them to consult an appropriate licensed clinician rather than self-diagnosing from a neuroscience explainer.
Related: How Does the Brain Learn? · How Does the Brain Form Memories? · How Does the Brain Make Decisions?
References
- Yin HH, Knowlton BJ. The role of the basal ganglia in habit formation. Nature Reviews Neuroscience. 2006;7(6):464-476.
- Graybiel AM. Habits, rituals, and the evaluative brain. Annual Review of Neuroscience. 2008;31:359-387.
- Balleine BW, O’Doherty JP. Human and rodent homologies in action control: corticostriatal determinants of goal-directed and habitual action. Neuropsychopharmacology. 2010;35(1):48-69.
- Lally P, van Jaarsveld CHM, Potts HWW, Wardle J. How are habits formed: modelling habit formation in the real world. European Journal of Social Psychology. 2010;40(6):998-1009.
- Wood W, Rünger D. Psychology of habit. Annual Review of Psychology. 2016;67:289-314.
Written by: MedMaru Editorial Team
Reviewed for medical accuracy by:
S. Chang, KMD