How Does the Brain Process Touch?
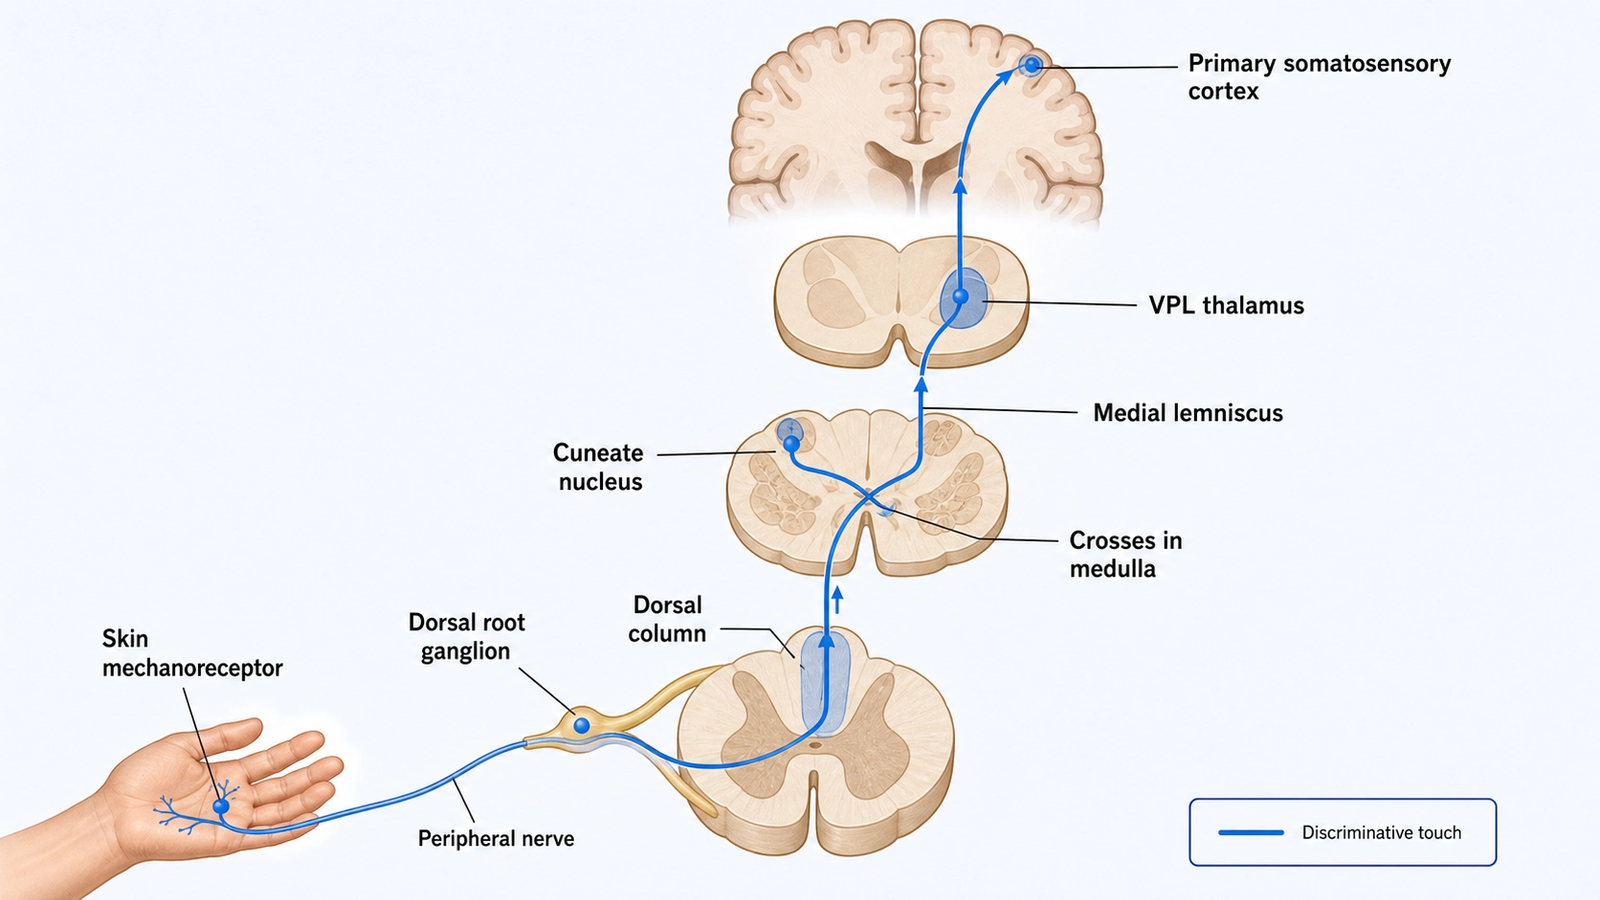
Touch begins in your skin, but it becomes a perception only after a relay through nerves, the spinal cord or brainstem, the thalamus, and the cortex. Tiny sensors in the skin called low-threshold mechanoreceptors respond when the skin is pressed, vibrated, stretched, or moved. Sensory neurons carry these signals toward the spinal cord. Fine, discriminative touch from the body then travels mainly along a route called the dorsal column–medial lemniscus pathway, up to a part of the thalamus called the ventral posterior lateral nucleus, and on to the primary somatosensory cortex. Touch from the face takes a separate route through the trigeminal pathways. In the cortex, networks keep an organized map of the body and combine touch with body position, vision, attention, and movement.
Many sensors, many features
Touch is not really one sense. It is a family of related signals, including pressure, vibration, stretch, texture, and movement across the skin. Pain and temperature use overlapping but distinct receptors and pathways.
The mechanoreceptors that serve touch differ in how large an area of skin each one covers, how deep it sits, and how quickly it adapts. Some respond strongly when contact begins or ends. Others keep signaling as long as the pressure lasts. Think of a team of reporters, each covering a different angle of the same event. Together, large populations of receptors encode edges, texture, vibration, skin stretch, and the movement of objects across the skin. The analogy has limits, since receptors don’t choose their stories, but it captures the division of labor. Each receptor turns mechanical deformation into an electrical change, a process called mechanotransduction.
An organized code on the way up
The first neurons in the chain have their cell bodies in clusters next to the spinal cord, called dorsal root ganglia, for the body, and in the trigeminal ganglia for much of the face. Many discriminative touch signals travel along myelinated fibers, which are insulated and therefore fast. No single receptor carries a complete touch experience. What you feel is represented by patterns of activity spread across many fibers.
Signals from the body climb on the same side of the spinal cord in the dorsal columns until they reach the gracile and cuneate nuclei in the lower medulla. There, second-order neurons send their axons across to the other side, and these crossed fibers rise as the medial lemniscus to the ventral posterior lateral nucleus of the thalamus. Thalamic neurons then project to the primary somatosensory cortex. This is the textbook route, and it is a useful simplification rather than an exclusive cable. Crude touch can also be carried in the anterolateral pathways.
A map of the body in the cortex
The primary somatosensory cortex lies in the postcentral gyrus, a ridge just behind the middle of the brain’s surface. Neighboring areas of cortex often represent neighboring parts of the body, so the cortex holds a kind of body map. The map is not to scale. Body parts with many receptors and fine discrimination take up disproportionately large territory. That is why fingertips are so sensitive: they combine dense receptors, small receptive fields, and a large share of the cortical map. The map is also dynamic. Attention, use, injury, and learning can all change how its neurons respond.
Touching is also moving
Recognizing an object by handling it takes more than input from the skin. Think of finding your keys in a bag without looking. Your brain combines touch signals with the position of your fingers, the movement commands it is sending, and your memory and expectations of what keys feel like. When you can see, vision joins in too. This active exploration is why touch and movement are so tightly linked in the brain.
When the touch pathway is damaged
Because touch passes through so many stations, damage at different points produces different patterns. A lesion in a peripheral nerve, a spinal pathway, the thalamus, or the cortex can each cause a different pattern of numbness or impaired discrimination.
This article is educational background, not a diagnostic guide. Sudden numbness on one side of the body, especially with weakness, speech difficulty, facial droop, or a severe headache, requires emergency evaluation.
Related: How Does the Brain Process Pain? · How Does the Brain Process Sensory Information? · What Is Proprioception? How Your Brain Knows Where Your Body Is
References
- Purves D, Augustine GJ, Fitzpatrick D, et al. The Major Afferent Pathway for Mechanosensory Information: The Dorsal Column–Medial Lemniscus System. Neuroscience. NCBI Bookshelf
- Raju H, Tadi P. Neuroanatomy, Somatosensory Cortex. StatPearls. NCBI Bookshelf
- Whitehead C, Grider MH. Neuroanatomy, Touch Receptor. StatPearls. NCBI Bookshelf
Written by: MedMaru Editorial Team
Reviewed for medical accuracy by:
S. Chang, KMD